I’m a Miner!
Author: Dr. José Valencia. Unidad de Hemodinámica – Hospital General Universitario Dr. Balmis. Alicante. Spain
A male 54 years old with hypertension, type 2 Diabetes, dyslipidemia, active smoking, severe alcoholism and no previous cardiac history.
He was transfered with an inferior STEMI for primary PCI.
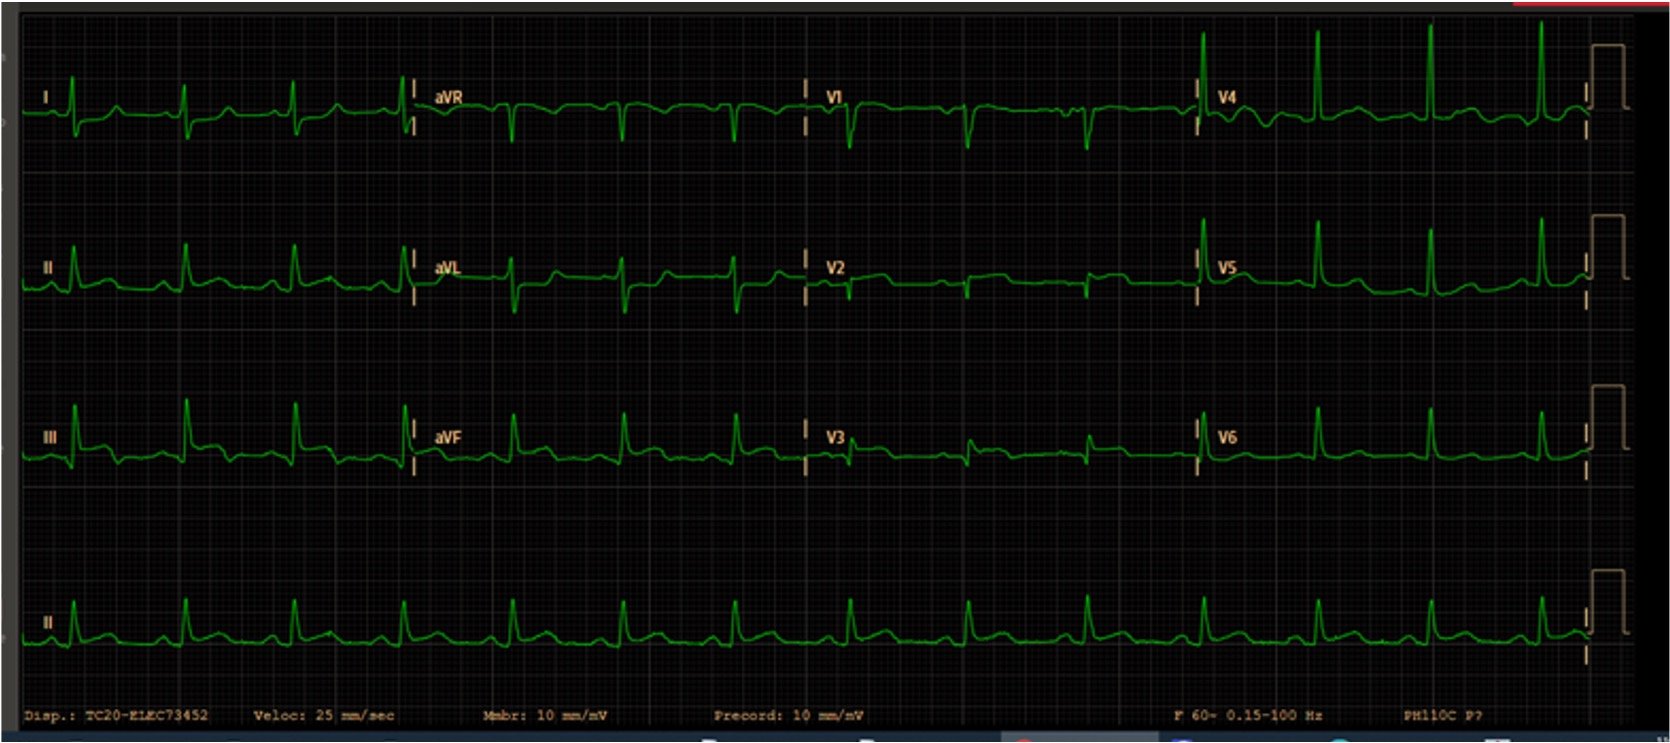
The RCA was heavely calcifed at the three main segments, so several attempts were done to get the distal vessel
Double wire
Even with a Finecross Microcateter
Pilot 50 over Finecross
Finecross & Sion Black
Finally Predilatation was done with 2mm NC balloon
Finally, predilatation with a 3 mm NC Balloon was performed with this result
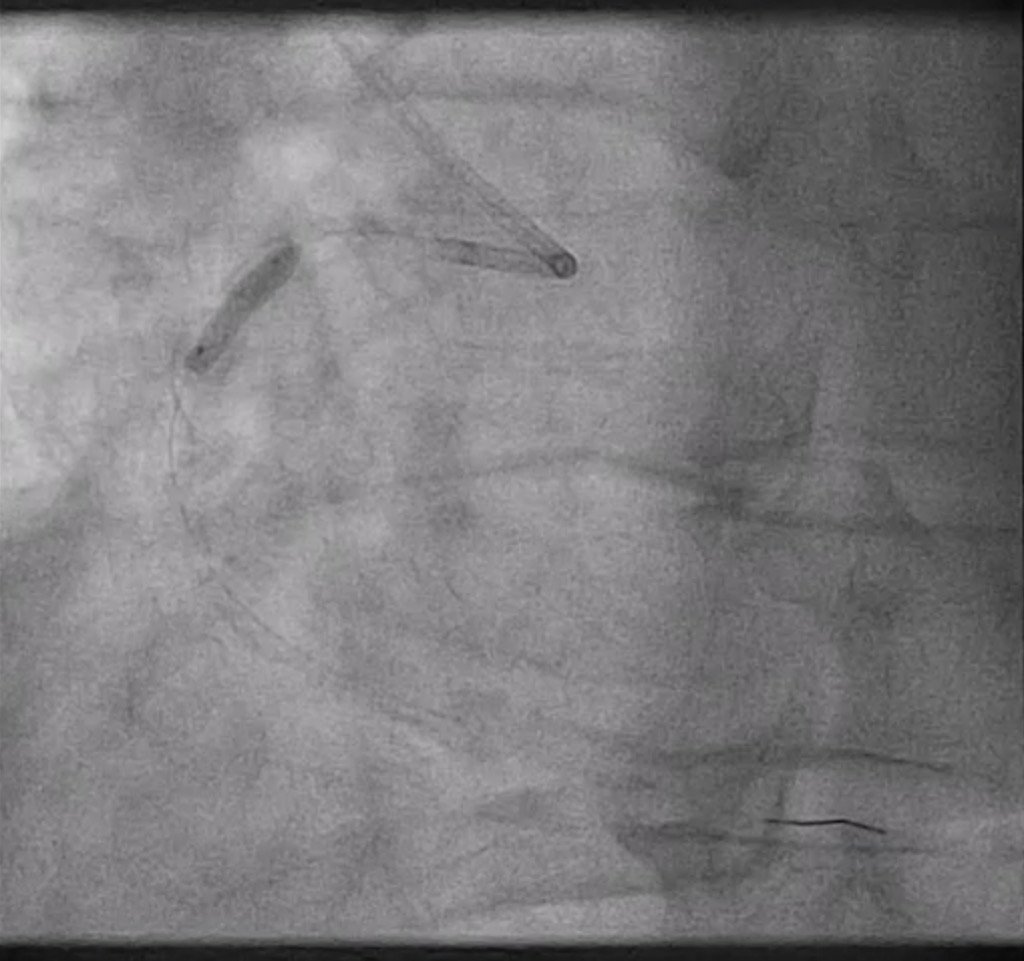
As we could not go forward with any device so we decided to perform ELCA with a 0.9mm catheter at mid segment of the RCA(501 seg, 38812 pulses, saline infusion)
Later, we could not cross distally with any balloon and the result was this ECG
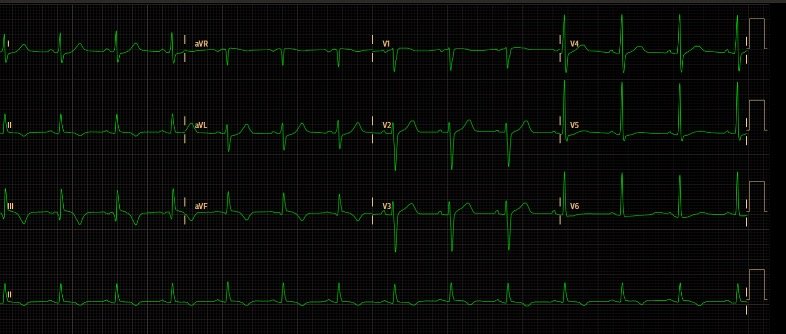
And this angiographic result.
What would you do?
- Go on with another plaque modification technique?
- Leave it as it is?
- Leave it for a second try?
- Surgery?
The patient was at the ICU with good clinical evolution so a new angiography was performed in the following days.
Rotational atherectomy was performed with 1.5 and 1.75 mm burs as well as balloon predilation.
The OCT showed extreme calcification, in some segments they were circumferential with several grades of thickness, multiple eruptive nodules, and fractures caused by the plaque modification therapies used.


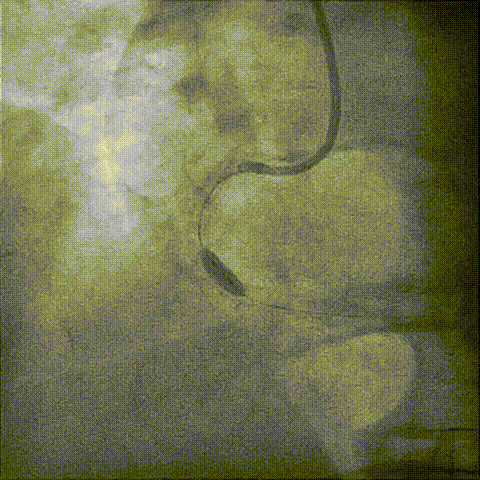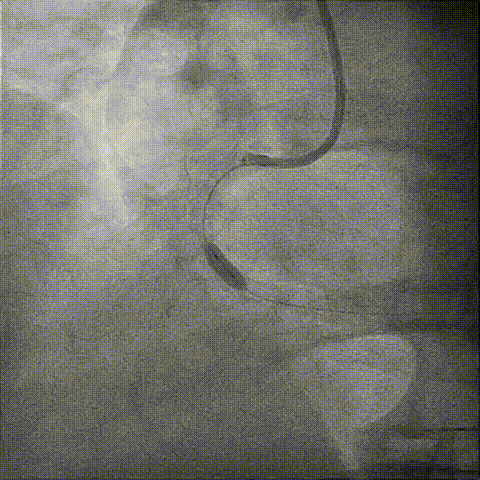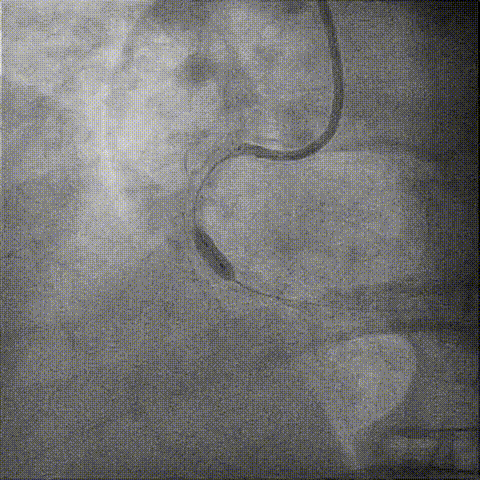
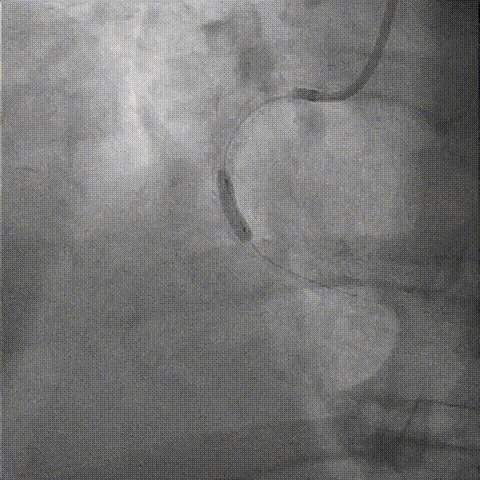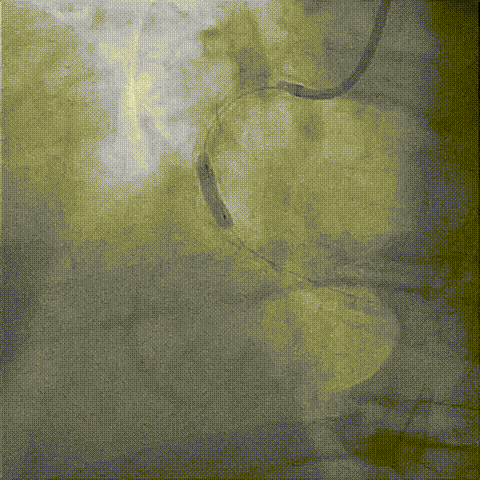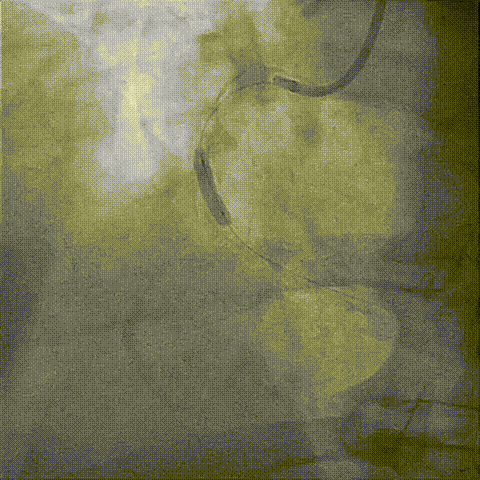


3.5 mm Shockwave, Wolverineballoons and 4 mm NC Balloonswere used for the proximal lesions
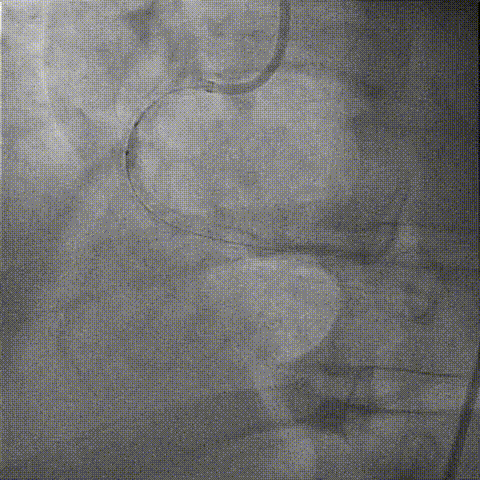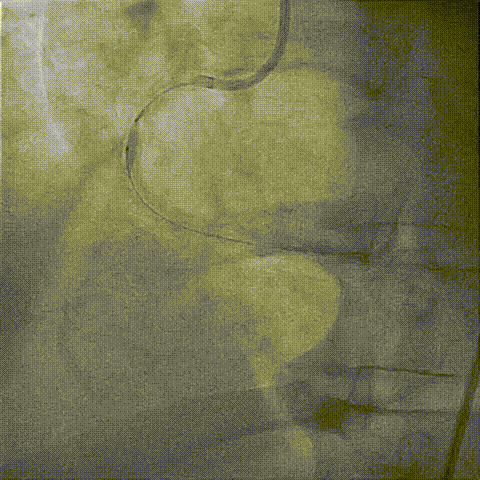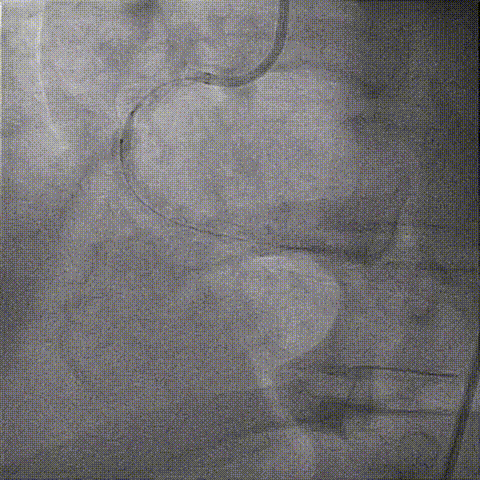
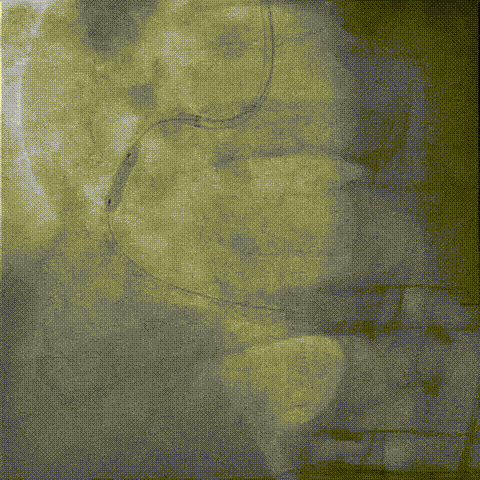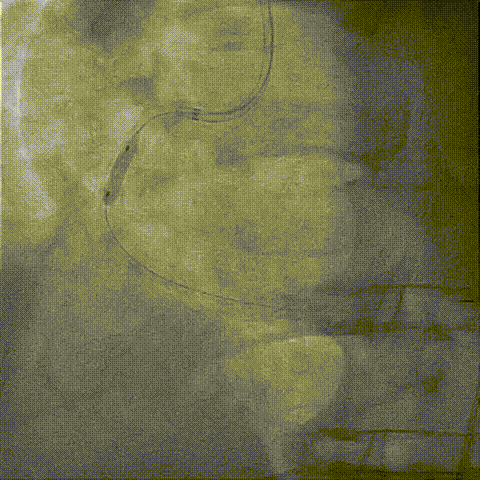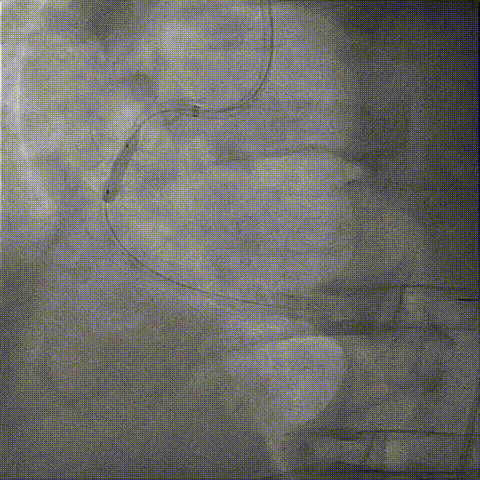
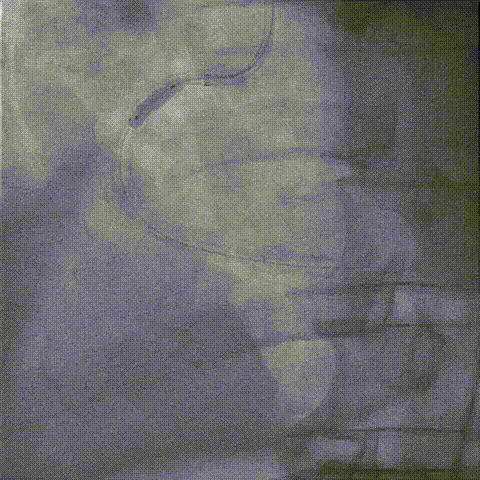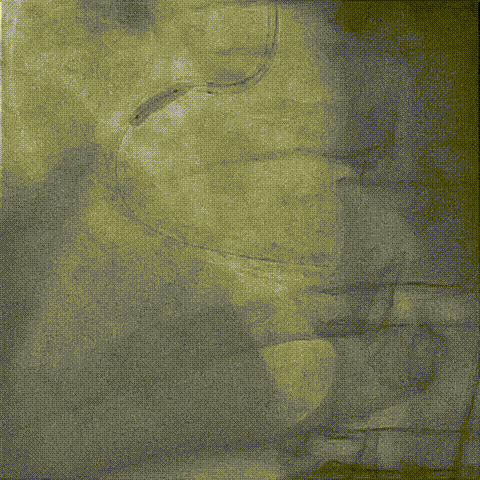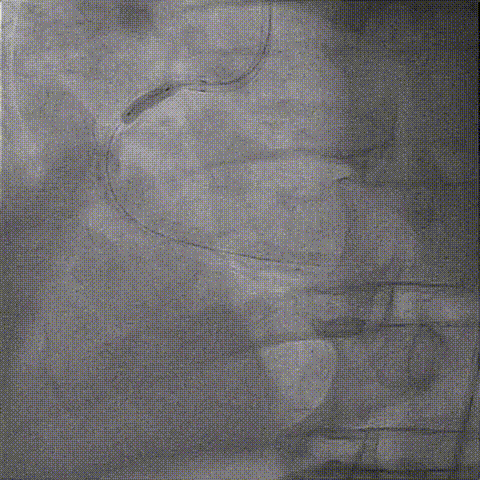
Finally, three overlapped Ultimaster Tansei stents (4 mm) were deployed with this result after postdilatation with 4,5mm NC balloon